Topiramate, and the FDA-approved combination phentermine/topiramate (Qsymia), can produce clinically meaningful weight loss when paired with diet, exercise, and medical monitoring. That benefit comes with real requirements: pregnancy testing, blood work, and attention to cognitive and metabolic side effects, all of which is why this medication is meant to be managed by a licensed prescriber, not self-directed.
TL;DR:
- The high-dose combination of phentermine and topiramate can lead to an average weight loss of about 9% to 11% over a year, with two-thirds of patients losing at least 5% of their starting weight.
- Most of the weight loss occurs within the first three to six months, and response is typically evaluated at 12 weeks to decide whether to continue or adjust treatment.
- Side effects like neurological numbness, cognitive fog, and taste changes are common and influence discontinuation more often than efficacy issues.
- Topiramate alone causes smaller weight loss, averaging 3.7 to 5.3 kg beyond placebo, but does not produce the same substantial effect as the combined therapy.
- Treatment eligibility requires meeting specific BMI criteria and involves regular monitoring, pregnancy testing, and managing side effects through supervised telehealth programs.
Table of Contents
- Does Topiramate Actually Work for Weight Loss?
- How Does Topiramate Cause Weight Loss?
- Who Qualifies for Topiramate-Based Weight Loss Treatment?
- What Are the Side Effects and Warning Signs to Watch For?
- Topiramate vs. GLP-1 Drugs: Which Works Better?
- What Does a Supervised Telehealth Care Pathway Look Like?
- When Does the Math Favor Topiramate Over Other Options?
- Get Evaluated for Weight Loss Treatment Without the Waiting Room
- Where to Verify This Information
- Sources
- FAQ
Does Topiramate Actually Work for Weight Loss?
The short answer is yes, but the size of the effect depends heavily on whether you’re taking topiramate alone or in the FDA-approved combination with phentermine. The clinical trial record is unusually deep for an obesity drug, and it points in one consistent direction.
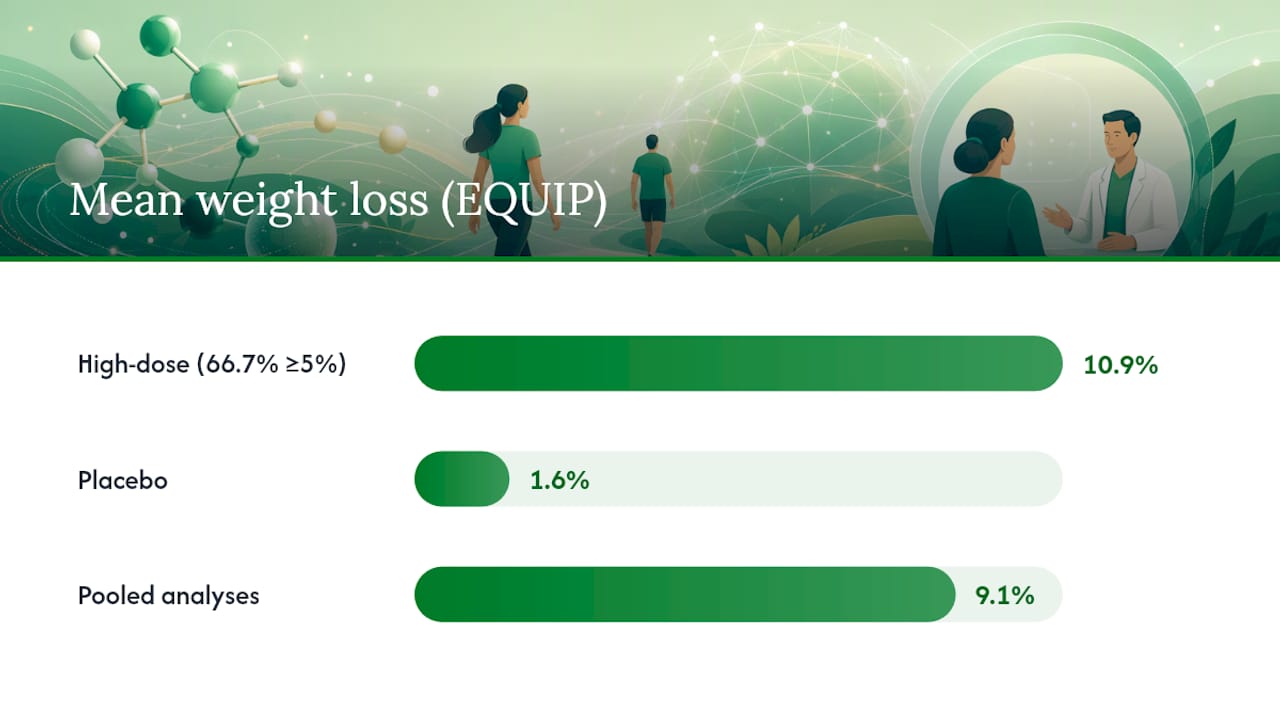
The pivotal EQUIP trial, a 56-week randomized controlled study in adults with severe obesity, found that people on the higher dose of phentermine/topiramate (15 mg/92 mg) lost a mean of 10.9% of their baseline body weight, compared with 1.6% for placebo. Two-thirds of that high-dose group lost at least 5% of their starting weight. That’s not a marginal effect. It’s one of the larger weight-loss signals ever recorded for an oral, non-injectable obesity medication.
The results weren’t a one-off. A separate 56-week phase 4 trial conducted in Korean adults with obesity found a significant percentage change in body weight versus a smaller percentage for placebo at week 56, with a notably higher proportion of treated participants reaching the 5% weight-loss threshold compared to placebo. Different population, different continent, remarkably similar outcome.
Topiramate on its own, without phentermine, works too, just with a smaller punch. Meta-analyses of topiramate monotherapy trials found roughly 3.7 to 5.3 kilograms of additional weight loss versus placebo, depending on the dose and how long people stayed on it. That’s meaningful for some patients, but it’s a fraction of what the combination therapy delivers, which is exactly why phentermine/topiramate, not topiramate alone, carries the FDA weight-loss indication.
A closer look at the numbers:
- EQUIP (56 weeks, high dose): 10.9% mean weight loss vs. 1.6% placebo, with 66.7% of patients losing ≥5%
- QUEEN’s study (56 weeks, Korean cohort): 8.3% mean weight loss vs. 2.3% placebo, with 68.5% reaching ≥5%
- Topiramate alone: roughly 3.7 to 5.3 kg beyond placebo, dose-dependent
- Broader comparative data places phentermine/topiramate’s average effect near 9.1% total body weight loss across pooled analyses
The headline number: Across multiple independent trials, the high-dose combination therapy consistently produces weight loss in the 8% to 11% range over roughly a year, a result that has held up across different patient populations and study designs.
Timing matters almost as much as magnitude. Most trial protocols check response at 12 weeks, and that checkpoint isn’t arbitrary. It’s baked into the FDA label as the decision point for whether to continue, increase, or stop the medication. Weight loss tends to be steepest in the first three to six months, then plateaus somewhat, though most of the trial cohorts kept losing weight gradually all the way through week 56.
Tolerability tracks with dose. Dropout rates in EQUIP and similar trials were higher in the high-dose arms, driven mostly by neurological side effects like tingling sensations and cognitive fog rather than anything life-threatening. Still, the fact that a meaningful share of participants stopped treatment because of how it made them feel, not because it didn’t work, tells you something important about the trade-off you’re weighing.
How Does Topiramate Cause Weight Loss?
Nobody has fully mapped the exact mechanism, but the leading theories point to several overlapping effects rather than one single switch being flipped.
Topiramate appears to reduce calorie intake by dampening activity in brain reward circuits tied to food, which may explain why many patients report that food simply feels less compelling rather than actively unappetizing. A narrative review of topiramate’s role in weight reduction describes effects on decreased fat accumulation and altered taste perception (a common side effect where carbonated drinks taste flat) that likely reduce intake of calorie-dense beverages specifically. Topiramate also inhibits carbonic anhydrase, an enzyme involved in acid-base balance, which is the same mechanism behind the metabolic acidosis risk discussed later.
Phentermine works through a completely different pathway. It’s a sympathomimetic amine, meaning it triggers a mild adrenaline-like response that suppresses appetite and modestly increases energy expenditure, similar to how amphetamines were once prescribed for weight loss decades ago, minus most of the abuse potential at prescribed doses.
Putting the two together is where the combination earns its bigger effect size:
- Topiramate targets reward-driven eating and taste preference
- Phentermine targets hunger signaling and modestly raises metabolic rate
- The two mechanisms don’t overlap, so their effects appear to be additive rather than redundant
- Lower doses of each drug in combination reduce side-effect burden compared to using either at a higher solo dose
That last point explains why Qsymia is formulated the way it is. Combining smaller doses of two different mechanisms achieves more weight loss with fewer side effects than pushing either drug to its individual ceiling.
Who Qualifies for Topiramate-Based Weight Loss Treatment?
Eligibility follows specific criteria set by the FDA label, not a general “wants to lose weight” standard. According to the Qsymia prescribing information, the medication is indicated for adults with a body mass index of 30 or higher, or a BMI of 27 or higher when combined with at least one weight-related condition such as high blood pressure, type 2 diabetes, or high cholesterol. It’s also approved for adolescents ages 12 to 17 with a BMI at or above the 95th percentile for age and sex, though pediatric prescribing requires extra caution around growth and bone density monitoring.
Here’s how the process typically unfolds once you qualify:
- Baseline evaluation. Your prescriber reviews your medical history, current medications, and orders baseline labs, including a pregnancy test if you’re of reproductive potential.
- Starting dose. Treatment usually begins with a low dose (3.75 mg/23 mg) for 14 days to ease tolerability before stepping up.
- Titration to standard dose. After two weeks, the dose typically increases to 7.5 mg/46 mg, the standard therapeutic dose for most patients.
- 12-week checkpoint (the 3% rule). If you haven’t lost at least 3% of baseline body weight by week 12 on the standard dose, the label calls for either discontinuing the medication or escalating to the higher dose.
- Higher dose and second checkpoint (the 5% rule). If escalated to 15 mg/92 mg, a second evaluation at 12 weeks on that dose checks for a 5% weight-loss response. Falling short at that point signals it’s time to stop, since continuing without response mainly adds side-effect risk with no added benefit.
- Ongoing monitoring. Periodic bloodwork continues throughout treatment, and discontinuation is done gradually rather than abruptly, since stopping topiramate suddenly can lower the seizure threshold in susceptible people.
Because of the REMS (Risk Evaluation and Mitigation Strategy) program tied to this medication, anyone of reproductive potential needs a negative pregnancy test before starting, monthly counseling on contraception use, and ongoing pregnancy testing during treatment. Baseline and periodic labs typically include serum bicarbonate, creatinine, and electrolytes, particularly important for anyone with existing kidney concerns, since dose adjustments are required for renal or hepatic impairment.
Pro Tip: Bring a full list of your current medications, including over-the-counter supplements, to your first visit. Topiramate interacts with several common drugs, and your prescriber needs the complete picture before setting your starting dose.
What Are the Side Effects and Warning Signs to Watch For?
Most people who start this medication will notice something within the first few weeks, and most of it is manageable rather than dangerous. The most frequently reported effects include tingling or numbness in the hands and feet (paresthesia), dry mouth, constipation, altered taste (especially with carbonated beverages), trouble sleeping, and some degree of cognitive fog, things like word-finding trouble or slower mental processing. These tend to be dose-dependent and often improve somewhat after the first few months, though for some patients the cognitive effects are the reason they eventually stop treatment altogether.
The more serious risks are less common but require real attention:
- Fetal harm. First-trimester exposure to topiramate raises the risk of orofacial clefts in the developing fetus, which is the entire reason behind the REMS pregnancy testing and contraception requirements.
- Acute myopia and secondary angle-closure glaucoma. This is a rare but urgent complication that typically appears within the first month of treatment and causes sudden vision changes and eye pain. It requires immediate medical attention.
- Metabolic acidosis. Topiramate can cause the body to lose bicarbonate, and untreated acidosis can eventually contribute to kidney stones and bone problems, which is why periodic bicarbonate monitoring is standard practice, not an optional extra.
- Mood changes and suicidal thoughts. Like several anticonvulsants, topiramate carries a labeled warning for new or worsening depression and suicidal ideation, particularly worth flagging if you have a personal history of mood disorders.
- Kidney stones. The same mechanism behind metabolic acidosis increases the risk of nephrolithiasis, especially in people with a prior history of stones.
Roughly two-thirds of patients on the high-dose combination in EQUIP achieved clinically meaningful weight loss, but tolerability, not efficacy, was the main reason people in the higher-dose group left the trial early.
Certain combinations deserve extra caution. Topiramate combined with valproic acid raises the risk of ammonia buildup and encephalopathy. Combining it with other antidiabetic medications can increase hypoglycemia risk, requiring closer glucose monitoring. Alcohol and other central nervous system depressants amplify the sedation and cognitive slowing that topiramate can already cause on its own.
Treat these as reasons to call your prescriber right away, not to wait for your next scheduled visit: any sudden vision change or eye pain, a positive pregnancy test, new or worsening depression or thoughts of self-harm, and cognitive impairment severe enough to interfere with work or driving.
Topiramate vs. GLP-1 Drugs: Which Works Better?
Phentermine/topiramate holds its own among oral weight-loss medications, but it isn’t the strongest option on the market overall. Pooled comparative data places its average effect around 9.1% total body weight loss, ahead of liraglutide and bupropion/naltrexone among other approved oral and injectable options. Semaglutide, one of the GLP-1 receptor agonists, tends to produce larger average losses, with indirect comparisons putting it closer to 13.7%.
That efficacy gap doesn’t automatically make GLP-1 drugs the better choice for every patient. Here’s how the trade-offs actually break down:
- Route of administration. Phentermine/topiramate is a daily pill; most GLP-1 medications, including how tirzepatide works for weight management, require weekly injections. Needle aversion is a real factor for some patients.
- Side-effect profile. GLP-1s are more associated with nausea and gastrointestinal symptoms; phentermine/topiramate carries more neurological and cognitive risk.
- Monitoring burden. Topiramate-based therapy requires bicarbonate checks and REMS pregnancy protocols; GLP-1 monitoring focuses more on GI tolerance and, for some patients, pancreatic or gallbladder symptoms.
- Cost and access. Oral generics and Qsymia are often less expensive out-of-pocket than branded injectable GLP-1s, and insurance coverage patterns for each vary widely by plan.
- Pregnancy planning. Anyone actively trying to conceive faces a harder restriction with topiramate-based therapy given the fetal risk, which sometimes tips the decision toward a different weight-loss injection instead.
Clinicians often reach for phentermine/topiramate when a patient prefers an oral medication, has cost or coverage constraints around injectables, or has already tried a GLP-1 without success. It remains a legitimate first-line option in the right clinical context, not a fallback for when “better” drugs aren’t available.
What Does a Supervised Telehealth Care Pathway Look Like?
Starting this medication remotely follows the same clinical rigor as an in-person visit, just delivered through video and messaging instead of a waiting room. A proper initial evaluation covers your weight history, prior attempts at weight loss, current medications, any history of kidney stones or glaucoma, and mood history, plus a pregnancy test before the first prescription is sent if that applies to you.
Follow-up visits are built around the same checkpoints the FDA label describes: a review at 12 weeks to check the 3% response threshold, a possible dose increase, and another check further out for the 5% threshold. Labs, typically bicarbonate, creatinine, and electrolytes, get ordered and reviewed between visits rather than only at the start.
Telehealth handles prescribing, dose titration, lab ordering, and routine monitoring well. What it can’t replace is urgent in-person care for the red-flag symptoms already covered: sudden vision changes need an eye specialist immediately, not a message thread.
Pro Tip: Have your most recent weight, blood pressure reading, and any prior lab results (especially kidney function tests) ready before your first virtual visit. It speeds up your evaluation and helps your prescriber set an appropriate starting dose from day one.
- Initial visit: history, medication review, pregnancy test if applicable, baseline labs ordered
- Weeks 2 to 12: titration monitoring, side-effect check-ins
- Week 12: response evaluation against the 3% checkpoint
- Ongoing: periodic labs, dose reassessment, and refill management through the platform
When Does the Math Favor Topiramate Over Other Options?
Phentermine/topiramate tends to make the most sense for patients who want an oral option, have cost or insurance barriers to injectable GLP-1s, or have comorbidities like binge-eating patterns where the appetite-dampening effect is particularly useful. It’s a reasonable place to start rather than a last resort.
That said, if someone has diabetes where a GLP-1’s added glycemic benefit matters, is actively planning pregnancy, or has a personal history of kidney stones or glaucoma, the calculus often shifts toward GLP-1 therapy or, for higher BMI categories, bariatric surgery. At your appointment, ask directly about your eligibility under the label criteria, what monitoring schedule you’ll follow, how contraception planning fits your situation, and what the realistic alternative options look like given your specific health history.
— Bryan
Get Evaluated for Weight Loss Treatment Without the Waiting Room
Getting started on a medication like phentermine/topiramate shouldn’t require weeks of scheduling delays just to have a conversation about eligibility. Same-day virtual appointments for weight loss care are available, allowing you to get evaluated, discuss whether this treatment fits your health history, and have lab orders placed without waiting for a traditional in-office slot to open up.
A visit through Zealthy’s weight loss program works the way any responsible prescribing process should: a licensed provider reviews your history, orders the appropriate baseline labs, and follows the same FDA label checkpoints and REMS pregnancy protocols covered throughout this article. Prescribers won’t prescribe when a medication is contraindicated for your specific situation, and treatment plans are built around your labs and response, not a one-size-fits-all prescription pad. If oral therapy isn’t the right fit, the platform also supports evaluation for injectable options and coordinates ongoing primary care needs alongside weight management. Check the weight loss FAQ for program specifics, or book your first visit to find out what you qualify for.
Where to Verify This Information
For deeper reading, consult the Qsymia FDA label, the EQUIP trial, and MedlinePlus.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
Sources
- Controlled-Release Phentermine/Topiramate in Severely Obese Adults: A Randomized Controlled Trial (EQUIP)
- Medications for obesity management: Effectiveness and value
- QSYMIA prescribing information (label) - 2023 supplement
- Evaluation of the efficacy and safety of controlled‐release phentermine/topiramate in adults with obesity in Korea: QUEEN’s study
- Phentermine and Topiramate: MedlinePlus Drug Information
FAQ
How quickly do you lose weight on topiramate?
Most measurable weight loss shows up within the first 12 weeks, which is why the FDA label uses that point to check for a 3% response on the standard dose. In the EQUIP trial, patients on the high-dose combination lost a mean of 10.9% of baseline weight by week 56, with most of that loss occurring in the first six months before leveling off.
What is better for weight loss, phentermine or topiramate?
Neither works as well alone as the combination does together, but phentermine alone tends to produce faster short-term appetite suppression while topiramate alone works more gradually through reward-circuit and taste effects. The FDA-approved combination, marketed as Qsymia, outperforms either drug individually, which is exactly why it carries the weight-loss indication rather than topiramate by itself.
What did Kelly Clarkson use to lose weight?
Kelly Clarkson has publicly discussed changing her diet and lifestyle habits as part of her weight-loss approach, but there is no verified, publicly confirmed medical record tying her results specifically to phentermine/topiramate or any other prescription weight-loss medication. Any specific medication claims tied to a celebrity’s weight loss should be treated skeptically unless confirmed by the person themselves or a credible medical source.
What should I avoid while taking topiramate?
Avoid alcohol and other central nervous system depressants, since they intensify the sedation and cognitive slowing topiramate can already cause. You should also avoid becoming pregnant while on this medication without first talking to your prescriber, given the risk of fetal harm in the first trimester, and flag any personal history of kidney stones or glaucoma before starting.
Can topiramate help with obesity even without phentermine?
Yes, topiramate alone produces weight loss beyond placebo, with meta-analyses showing roughly 3.7 to 5.3 kilograms of additional loss depending on dose. It’s a smaller effect than the combination therapy delivers, so it’s typically considered off-label use for weight management rather than a first-choice option when the combination is available and appropriate.


